

If you live with chronic pain, you’ve probably noticed it doesn’t behave the same way every day. It can flare when you’re stressed or exhausted and fade into the background when you’re absorbed in something you enjoy. The gate control theory of pain, proposed by Ronald Melzack and Patrick Wall in 1965, asks us to imagine a “gate” in the spinal cord that lets more or fewer pain signals through to the brain, depending on other nerve activity and signals coming down from the brain. It isn’t a treatment. It’s an explanation of how pain is adjusted along the way, and it’s shaped many of the pain management approaches used today.
What Is the Gate Control Theory of Pain?
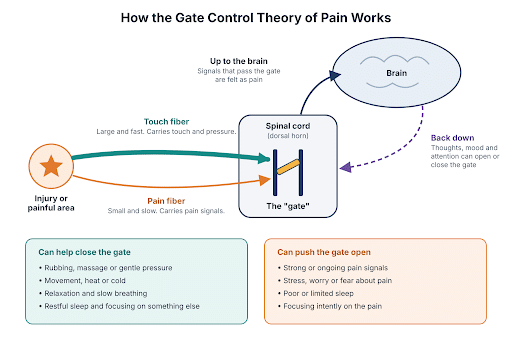
The gate control theory of pain says that pain signals don’t travel straight from an injury to the brain. They pass through a checkpoint in the spinal cord that can amplify or dampen them first. Touch, movement, emotions and attention can all influence how open that checkpoint is.
Before 1965, pain was widely viewed as a direct alarm: the more tissue damage, the more pain. Melzack and Wall’s theory offered a better explanation for everyday experiences that didn’t fit that model, such as why rubbing a bumped elbow helps, or why two people with the same injury can feel very different amounts of pain.
How Does Gate Control Theory Work?
The theory centers on an area of the spinal cord called the dorsal horn, where incoming nerve signals are processed before traveling to the brain. Different types of nerve fibers compete there, and the brain sends its own signals down to influence the result.
Large Fibers That Help Close the Gate
Large, fast nerve fibers carry information about touch, pressure and vibration. When they’re active, they can reduce how many pain signals get passed along. This is why rubbing or pressing on a sore spot often takes the edge off.
Small Fibers That Push the Gate Open
Smaller, slower fibers carry pain signals. When these fibers are highly active and there’s little competing input, more pain signals make it through to the brain.
The Brain’s Role
The brain doesn’t just receive pain signals. It also sends messages back down the spinal cord that can turn pain transmission up or down. Attention, mood, stress, expectations and past experiences all feed into those descending signals, which is why emotional state and focus can change how strongly pain is felt.
What Opens and Closes the Pain Gate?
Physical sensations, emotions and overall health can all influence the gate. None of these factors switches pain on or off, but each can nudge how intense it feels.
Factors that tend to help close the gate:
- Gentle touch, massage, pressure or vibration near the painful area
- Movement and regular physical activity
- Heat or cold applied to the area
- Relaxation, slow breathing and feeling calm
- Engaging activities, conversation or music that draw your attention elsewhere
- Restful sleep and a sense of social support
Factors that tend to open the gate:
- Ongoing stress, worry or fear about pain
- Low mood, frustration or feeling isolated
- Focusing intently on the pain or repeatedly checking how it feels
- Poor or limited sleep
- Ongoing inflammation or tissue injury
Examples of Gate Control Theory in Everyday Life
You’ve likely experienced gate control without knowing its name. Common examples include rubbing a stubbed toe, shaking out a hand after a pinch, or forgetting about a headache during an absorbing movie.
Rubbing or Massaging a Sore Spot
Pressing or rubbing an injured area activates the large touch fibers, which compete with pain signals at the spinal gate. Massage works on a similar principle.
Heat and Cold
A warm compress or cold pack adds competing temperature signals and can help muscles relax. Cold also reduces swelling after an acute injury.
TENS Units
A TENS (transcutaneous electrical nerve stimulation) unit sends mild electrical pulses through the skin. It was developed partly with gate control principles in mind. Many people use it, but the research is mixed. A 2019 overview of Cochrane reviews found the quality of evidence for chronic pain too low to say with confidence whether TENS helps. Talk with a provider about whether it’s worth trying for your condition.
Movement and Distraction
Gentle movement adds touch and position signals and can ease stiffness. Distraction works from the top down: when your attention is engaged elsewhere, the brain tends to give pain signals less priority.
How Is Gate Control Theory Used in Chronic Pain Management?
Gate control theory helps explain why pain care often combines several approaches instead of relying on one. Treatments that add competing nerve input, calm the stress response or change how the nervous system processes pain all fit within the framework. They are tools that can help, not guarantees.
Exercise and Physical Therapy
Staying active is one of the most widely recommended nondrug approaches for chronic pain. According to the National Center for Complementary and Integrative Health (NCCIH), yoga has shown benefits for low back pain in the short and intermediate term, and tai chi may decrease pain intensity and improve everyday function.
Mindfulness and Relaxation
Mindfulness and relaxation practices target the brain’s role in the gate. NCCIH reports that mindfulness-based interventions can help decrease pain intensity and improve physical functioning in chronic pain. It also notes moderate-quality evidence for mindfulness-based stress reduction in low back pain. Progressive muscle relaxation is among the nondrug approaches suggested as a first step for chronic low back pain.
Biofeedback
Biofeedback uses sensors to show real-time information about muscle tension, heart rate or breathing, so you can learn to adjust those responses. NCCIH notes that biofeedback may moderately improve low back pain.
Sleep
Sleep and pain affect each other. Research published in the Journal of Neuroscience in 2019 found that sleep loss heightened pain sensitivity in healthy adults. Protecting sleep is one practical way to keep the gate from swinging wider.
Neuromodulation
The gate control theory also influenced the development of spinal cord stimulation, which sends mild electrical pulses to the spinal cord to interfere with pain signals before they reach the brain. Spinal cord stimulation may be considered for certain types of chronic pain when conservative treatments and medications haven’t provided enough relief. Whether it’s an option for you depends on a detailed evaluation.
Does Gate Control Theory Mean Pain Is “All in Your Head”?
No. Gate control theory confirms that pain is real and rooted in the nervous system. It shows that the brain and spinal cord actively shape how strongly pain is felt, which is very different from saying pain is imagined.
This distinction matters for people with chronic pain, who are sometimes told their symptoms are exaggerated. Understanding that stress, sleep and attention affect pain signals doesn’t mean you can or should simply think your pain away. It means there are several ways to support your nervous system alongside medical care.
Building a Personal Approach
Because pain is shaped by many factors, the most useful approach is one built around your condition, triggers and daily life. A few practical starting points:
- Keep a simple pain diary to track what seems to make pain better or worse
- Try one gate-closing strategy at a time, such as heat, gentle movement or slow breathing, so you can tell what helps
- Make sleep a priority. The CDC recommends at least seven hours a night for adults
- Combine physical, emotional and lifestyle strategies instead of relying on just one
- Be patient. Changes in chronic pain often happen gradually, and bad days don’t mean a strategy has failed
Self-management works best alongside professional care, not instead of it.
When To See a Pain Management Specialist
A pain management specialist can help when self-care strategies aren’t enough on their own. Consider making an appointment if:
- Your pain has lasted longer than three months or keeps coming back
- Pain is limiting your sleep, work or ability to stay active
- Pain travels into your arms or legs, or comes with numbness, tingling or weakness
- You’re relying on pain medication more than you’d like
- You want a coordinated plan that includes options beyond medication
Seek immediate care for sudden severe pain, pain after a serious injury, or pain with loss of bladder or bowel control.
Chronic Pain Care at Summit Spine & Joint Centers
At Summit Spine & Joint Centers, chronic pain care starts with understanding where your pain comes from and what affects it. Our board-certified physicians, many with fellowship training in fluoroscopically guided spine interventions, build personalized plans that may combine medication management, rehabilitation and minimally invasive procedures such as radiofrequency ablation. Find the pain management clinic near you or talk to a specialist at (844) 972-7752.
Gate Control Theory of Pain FAQs
Simply put, the gate control theory of pain says there’s a “gate” in the spinal cord that controls how many pain signals reach the brain. Touch, pressure and calming signals from the brain can help close it, while strong pain signals, such as stress and fear, can push it open. It explains why the same injury can feel more or less painful depending on what else is happening in your body and mind.
Common strategies include rubbing or massaging the sore area, using heat or cold, gentle movement, slow breathing, mindfulness and activities that hold your attention. Protecting your sleep and managing stress also help, since both affect how the nervous system handles pain. These strategies can ease pain for many people, but they work best as part of a broader plan, and they don’t replace evaluation for pain that is severe, persistent or getting worse.
The theory itself is an explanation, not a treatment, but many approaches that fit within it have research behind them. NCCIH reports evidence that mindfulness-based programs, yoga, tai chi and biofeedback can help with some types of chronic pain, especially low back pain. Spinal cord stimulation grew directly out of gate control ideas. Evidence for other tools, such as TENS, is less certain. Results vary from person to person, which is why a specialist’s input is valuable.
The classic example is rubbing your elbow after bumping it. The pressure activates large touch fibers that compete with pain signals at the spinal gate, so the pain eases. Getting so absorbed in a conversation or movie that you briefly forget a headache is another example, this time driven by signals from the brain.
Yes, though it has been refined. Researchers have since found that the specific spinal wiring Melzack and Wall proposed in 1965 is more complex than they described. The core idea, that pain signals are modulated in the spinal cord and influenced by the brain, remains foundational in pain science. It also helped inspire treatments such as TENS and spinal cord stimulation.